


Viagra for Bodybuilders: What the Evidence Actually Shows

There are plenty of legitimate reasons to use Viagra and its relatives beyond the obvious one — and some of them are genuinely interesting to bodybuilders. But the case is weaker than it is usually presented, and one of the three main claims made for these drugs is contradicted by the very study it is based on.
This article covers what PDE-5 inhibitors actually do, what the research supports, and what the risks are that get left out.
A short, accurate history
In the 1980s, researchers established that nitric oxide (NO) is a potent vasodilator — a discovery that won the 1998 Nobel Prize in Medicine for Furchgott, Ignarro and Murad. NO relaxes blood vessels, improving circulation and everything that depends on good blood flow.
That work led researchers to a class of drugs called PDE-5 inhibitors, which amplify and prolong NO's vasodilating effects by blocking the enzyme that breaks down cGMP. The target was angina.
Sildenafil citrate was the first of them, discovered by Pfizer in 1989. In angina trials it was only modestly effective — but trial participants reported an unexpected side effect with some frequency.
Pfizer moved quickly to pilot studies of sildenafil in erectile dysfunction. Those were a clear success. The company patented sildenafil in 1996, and the FDA approved Viagra on 27 March 1998 — barely two years later, an unusually short gap.
The cultural effect was real
Men who assumed that part of their life was over suddenly had it back. Perhaps more surprisingly, much younger men adopted the drug too, along with its chemical relatives Cialis (tadalafil) and Levitra (vardenafil) as those arrived.
They use them as a buffer against performance anxiety and to reduce the refractory period between sexual encounters. But there are other reasons — and some of them are related to training and body composition.
Claim 1: PDE-5 inhibitors increase the "pump"
Verdict: mechanistically plausible, but not demonstrated in bodybuilders.
The basic effect of these drugs is increased blood flow — not only to the heart and penis, but systemically, including to skeletal muscle. More blood flow means a fuller pump from resistance training, and in principle greater nutrient and oxygen delivery to working muscle.
Why the claim is weaker than it sounds:
· The mechanism is real, but the outcome is not studied. No trial has measured muscle pump, nutrient delivery or hypertrophy in bodybuilders taking PDE-5 inhibitors. The reasoning is sound; the evidence is absent.
· Vasodilation is systemic, not local. The drug does not direct blood to the muscle you are training.
· The "nutrient flow" argument is speculative. More blood passing through a muscle is not the same as more muscle protein synthesis.
This is the kind of claim that is reasonable as a hypothesis and should not be presented as a benefit. If it works, nobody has shown it.
Claim 2: PDE-5 inhibitors decrease estrogen levels
Verdict: the evidence points in both directions, and the strongest study found the opposite.
An earlier version of this article stated that 10 mg and 20 mg doses of Cialis, taken around ten times a month, significantly reduced estradiol — but only in men with a BMI under 27.
What that came from: a 2006 pilot study by Greco and colleagues, which found that 12 months of tadalafil was associated with an increased testosterone-to-estradiol ratio, mainly through a reduction in estradiol. That study is real, and that is what it found.
The problem: the same claim does not hold for the class. A larger study of sildenafil — 140 men, published in Andrology in 2013 — measured estradiol directly by mass spectrometry and found it increased, by 14 pmol/L (3.7 pg/mL, p < 0.001), in parallel with the rise in testosterone.
|
Study |
Drug |
Estradiol result |
|
Greco et al. 2006 (pilot) |
Tadalafil (Cialis) |
Decreased |
|
Spitzer et al. 2013 (n=140) |
Sildenafil (Viagra) |
Increased |
So "PDE-5 inhibitors decrease estrogen" is not a property of the class. It is one finding from one small pilot study on one drug, contradicted by a larger study on another. Presenting it as a general effect — and as a reason for bodybuilders to take these drugs — overstates what is known.
On the aromatase point: it is true that men with more body fat have higher aromatase activity and convert more testosterone to estradiol. That part is not in dispute. It just does not establish that these drugs lower estrogen.
Claim 3: PDE-5 inhibitors increase testosterone
Verdict: verified — but from a study whose design limits what it can prove.
This is the strongest of the three claims, and the numbers are specific. The Testosterone and Erectile Dysfunction trial administered an optimised dose of sildenafil to 140 men aged 40–70 with erectile dysfunction and low testosterone (total testosterone under 330 ng/dL, and/or free testosterone under 50 pg/mL) over 3–7 weeks.
Total testosterone rose by a mean of 3.6 nmol/L — 103 ng/dL (p < 0.001). Free testosterone rose by 110 pmol/L. DHT and estradiol rose alongside it.
So "around 100 points" is accurate. But three details matter more than the headline number:
1. There was no control group. The study was longitudinal, without a separate untreated comparison. A rise across the study period cannot be firmly attributed to the drug.
2. The men had erectile dysfunction and low testosterone. A 103 ng/dL rise in a hypogonadal man with ED is not evidence that the same happens in a healthy bodybuilder with normal testosterone.
3. LH was suppressed (a change of −1.3 units/L). That is an important signal — the testosterone rise came with lower gonadotropin drive, pointing to a direct effect on the testis rather than increased natural production. The authors also found androstenedione and oestrone rising, suggesting a possible adrenal effect.
The honest summary: sildenafil measurably raised testosterone in a specific, unhealthy population over a few weeks. Whether it does anything similar in healthy men — and whether it matters — is not established.
What the article left out: the risks
PDE-5 inhibitors are prescription drugs, not supplements, and the suggestion that they might be taken "consistently, like vitamins" is not a safe framing. The relevant risks:
· Nitrates are an absolute contraindication. Combining a PDE-5 inhibitor with nitrates (including recreational "poppers") can cause a sudden, life-threatening drop in blood pressure. This is the most important interaction in the class.
· Priapism. An erection lasting hours is a medical emergency that can cause permanent damage. It is rare, but it is why these drugs need a prescriber.
· Blood pressure and dizziness. PDE-5 inhibitors lower blood pressure. Fainting, dizziness and headache are common; alpha-blockers and some other medications compound the effect.
· Visual disturbance. Sildenafil also inhibits PDE6 in the retina, which is why temporary blue-tinted vision and light sensitivity occur. Rarely, serious visual events have been reported.
· Hearing loss has been reported rarely.
· Interactions with certain HIV medications, antifungals and grapefruit.
None of that is compatible with treating these drugs as a daily supplement. The evidence for bodybuilding benefit is thinner than the evidence for the risks.
What this means in practice
· The testosterone finding is real but comes from an uncontrolled study in men with ED and low testosterone.
· The estrogen claim is contradicted by a larger study on a different drug in the same class.
· The pump claim is plausible and unproven.
· The risks are well-documented and include a potentially fatal drug interaction.
If you are considering these drugs, the honest position is that the bodybuilding rationale is speculative and the medical rationale requires a prescriber.
FAQ
Do PDE-5 inhibitors increase the muscle pump?
Possibly — they increase blood flow systemically, so the mechanism is plausible. But no study has measured pump or muscle growth in bodybuilders taking them. It is a hypothesis, not a demonstrated benefit.
Do Viagra and Cialis lower estrogen?
The evidence conflicts. A 2006 pilot study found tadalafil reduced estradiol. A larger 2013 study of 140 men found sildenafil increased it. This is not a consistent class effect.
Do Viagra and Cialis raise testosterone?
Sildenafil raised total testosterone by a mean of 103 ng/dL in 140 men aged 40–70 with erectile dysfunction and low testosterone. The study had no control group, and those men were not healthy bodybuilders, so the result does not necessarily generalise.
Can I take Viagra every day for the gym?
That is not what the evidence supports. PDE-5 inhibitors are prescription drugs with real cardiovascular risks — including a dangerous interaction with nitrates. The bodybuilding rationale is speculative; the risks are documented.
What happens if you mix Viagra with nitrates?
A severe, potentially life-threatening drop in blood pressure. This combination is contraindicated. Nitrates include prescription angina medication and recreational "poppers".
Is Viagra safe for bodybuilders?
It is a prescription medicine with a real side effect profile, including priapism, blood pressure effects and visual disturbances. Whether it is appropriate for you is a question for a prescriber, not an article.
Do you need a prescription for Viagra?
Yes — sildenafil, tadalafil and vardenafil are prescription-only medicines in most jurisdictions. This site supplies products for laboratory research purposes.
Does Viagra help you build muscle?
No study shows that it does. The proposed mechanism — increased blood flow — is plausible but has not been tested for muscle growth in bodybuilders.
Where to buy PDE-5 inhibitors
This site's men's health range carries sildenafil (generic Viagra), tadalafil (generic Cialis) and vardenafil (generic Levitra) in a range of strengths and formats, including soft tabs and professional presentations.
If the testosterone angle is what interests you, note that the strongest evidence in this article points to a direct effect on the testis in men who were already hypogonadal — a different situation from using these drugs to enhance training.
This article is educational and is not medical advice. Sildenafil, tadalafil and vardenafil are prescription medicines. Combining PDE-5 inhibitors with nitrates can be fatal. Speak to a doctor before using any of these drugs.
References
· Spitzer M, Bhasin S, Travison TG, Davda MN, Stroh H, Basaria S. "Sildenafil increases serum testosterone levels by a direct action on the testes." Andrology 2013;1(6):913–918. — 140 men aged 40–70; total testosterone +3.6 nmol/L (103 ng/dL, p<0.001); estradiol +14 pmol/L (p<0.001); LH suppressed.
· Greco EA, et al. "Testosterone:estradiol ratio changes associated with long-term tadalafil administration: a pilot study." 2006. — T:E ratio increased, mainly through reduction of estradiol.
· Ghofrani HA, et al. "Sildenafil: from angina to erectile dysfunction to pulmonary hypertension and beyond." 2006. — FDA approval for ED in March 1998.
Articles
The question most people actually need answered is not how many fit in a year but how many your liver, lipids and hormone axis can recover from. Those two numbers are often different — and working out how many Anavar cycles per year you can safely run means knowing all three.
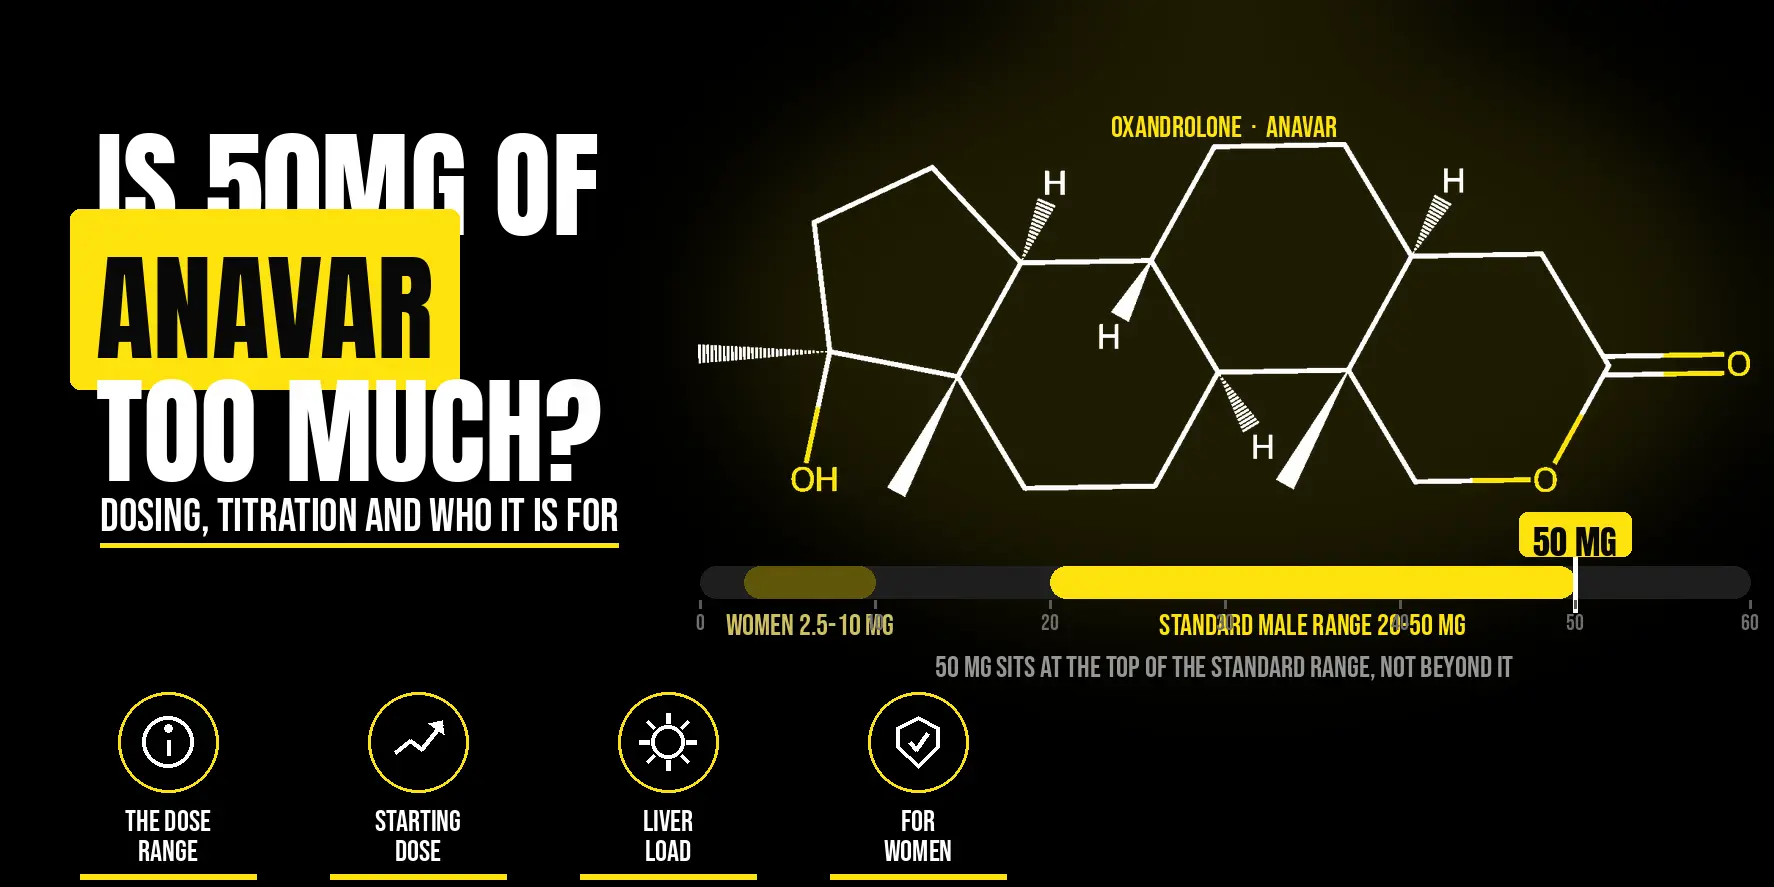
The useful answer depends on who is asking and what they are comparing it to. Below: where 50 mg sits on the dose range, why titration matters, and the liver and lipid considerations that come with any oral Anavar dose.

Worth noting before the numbers: TB-500 is not a steroid and does not build muscle. It is a repair peptide, and the dosing question is about tissue healing rather than performance.
PandaRoids Reviews
Please leave your review on products or service below.
For discounts, please contact us
- good
- ordering process it\'s easy, I don\'t see anything difficult here, even if you find a barrier guys will help you quick